
A small lump under the skin of the arm or hand, the leg or the ankle — painless, or sending small electric shocks when you press on it. The word "tumor" is alarming; it brings cancer to mind. Yet on a nerve, the vast majority of these masses are benign.
This article explains what these tumors are, why their treatment is a matter of precision — removing the mass without harming the nerve that carries it — and which rare signs should prompt a more thorough work-up.
A tumor on a nerve: what are we talking about?
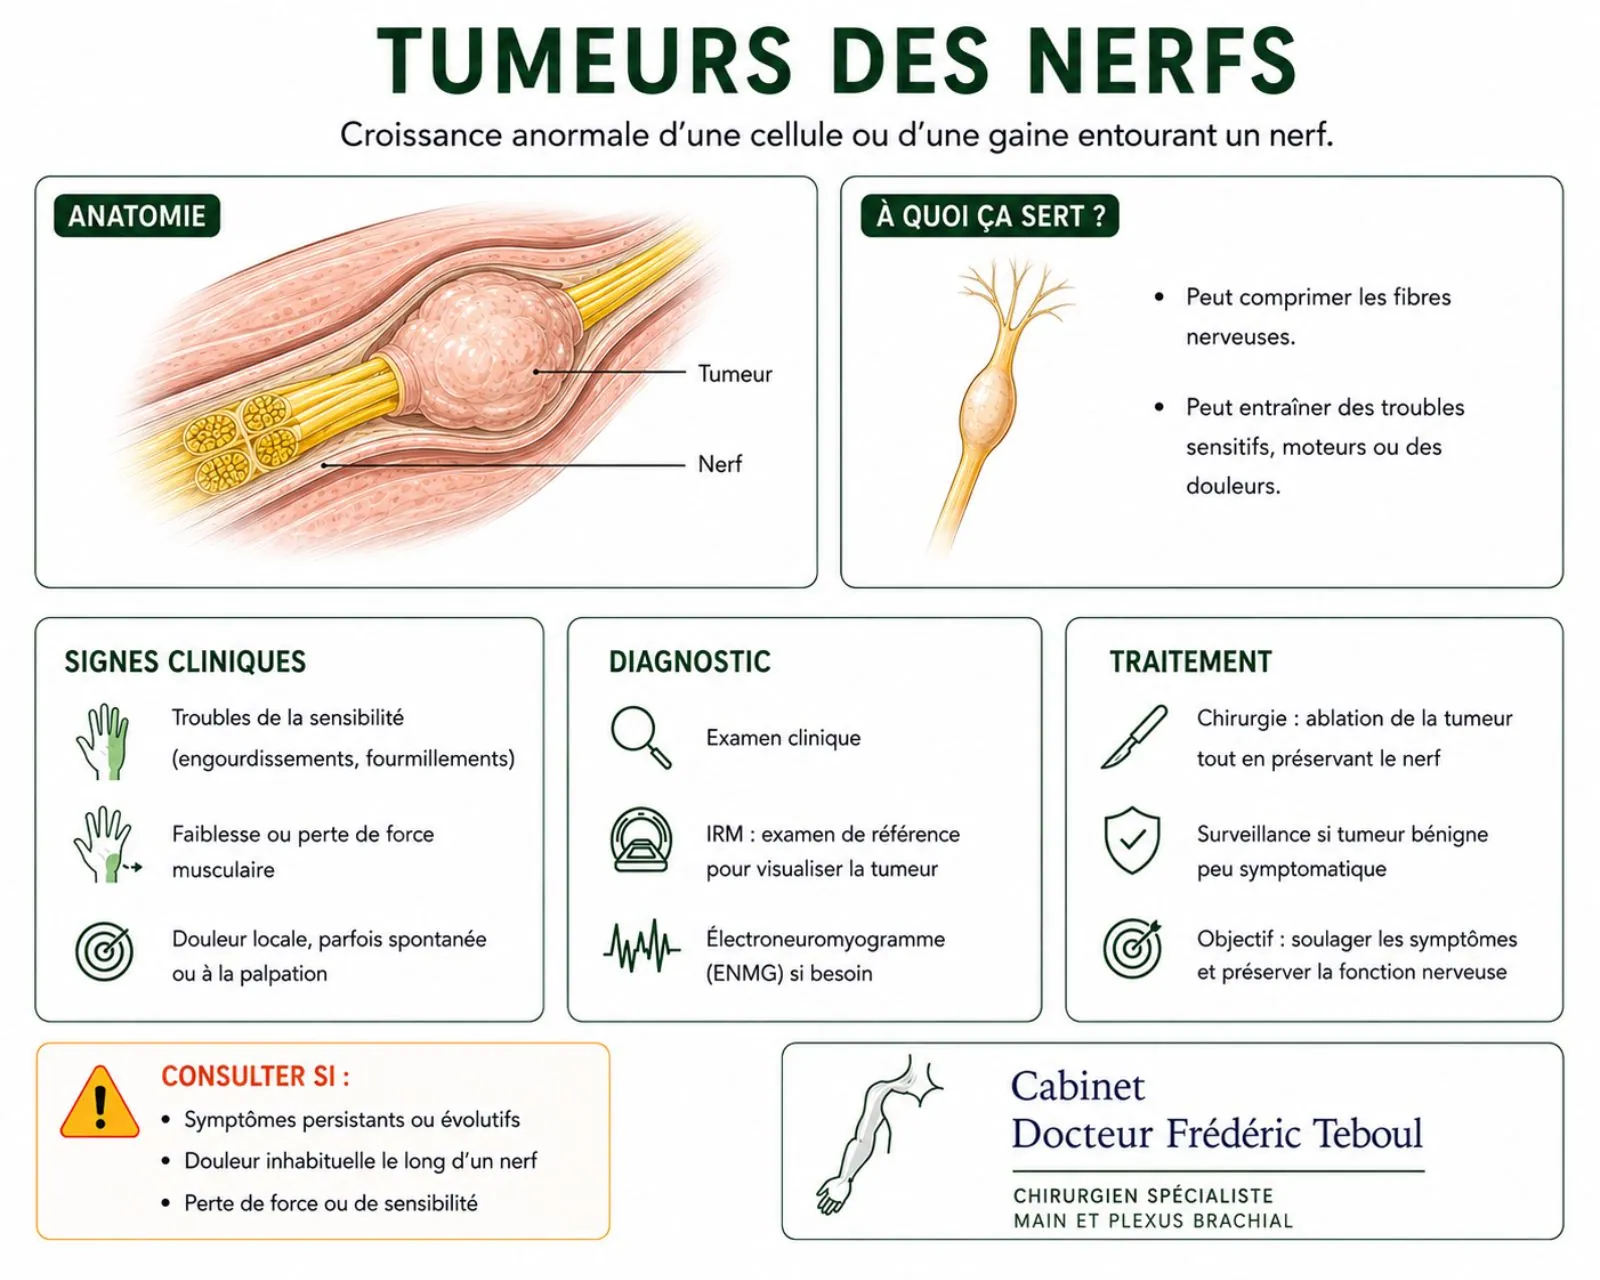
A nerve is made of fibers, grouped into bundles and surrounded by protective sheaths. A nerve tumor most often grows from these sheaths, not from the fibers themselves. This is an important point, because it explains why the tumor can often be removed without damaging the nerve.
The essential — and reassuring — message
These tumors are almost always benign. By far the most common is the schwannoma, a benign tumor that accounts for the great majority of nerve tumors. Next come neurofibromas, also benign. Malignant forms exist, but they are rare.
So finding a mass on a nerve is, in the vast majority of cases, not bad news.
Schwannoma and neurofibroma: a difference that matters for surgery
These two benign tumors feel similar to the patient, but their relationship to the nerve is different — and that changes how they are operated on.
The schwannoma
It grows alongside the motor and sensory nerve fibers, gradually stretching them apart. It is like a marble in a sheath: well defined, it can often be separated out and enucleated "like an eggshell" — removed while preserving the vital fibers.
The neurofibroma
It is more intertwined with the nerve fibers, from which it is harder to separate because it arises from them. Removing it is more delicate, as it risks taking functional fibers with it.
This distinction, made before and during the operation, guides the strategy: what is often straightforward for a schwannoma calls, for a neurofibroma, for a case-by-case discussion.
The symptoms: often subtle
These tumors grow slowly and stay silent for a long time. When they do show up, it is most often through:
A small mass under the skin, movable from side to side but little along the nerve, sometimes found by chance.
An electric shock or tingling in the nerve's territory when the mass is tapped or brushed — a sign that strongly points to its nerve origin.
Tingling or discomfort in the territory of the affected nerve.
More rarely, weakness when the tumor disrupts the nerve's conduction.
This little-shock-on-tapping sign is especially useful: it links the mass to a nerve, which points the diagnosis and management in the right direction from the start. See the article on lumps and cysts of the fingers.
Diagnosis: mapping before acting
The work-up has a twofold goal: to confirm the nerve origin and, above all, to map precisely how the tumor relates to the nerve, in order to prepare safe surgery.
It locates the mass along the course of a nerve, looks for the shock on tapping and any deficit.
It identifies the mass and its connection to the nerve.
This is the key exam: it defines the size, depth, and exact relationship to the nerve, and helps tell a well-defined benign tumor from a suspicious lesion.
It makes it possible to pinpoint the lesion in relation to the surrounding structures.
An important point
A presumed schwannoma is not biopsied lightly. Needling a clearly identified benign tumor to take a fragment risks damaging the nerve fibers and causing a palsy, with no benefit.
Biopsy is reserved for situations where a malignant form is suspected, and it is then carefully planned. For a typically benign-looking tumor, imaging is enough to decide.
Treatment: removing the tumor, keeping the nerve
This is the whole art of this surgery, and what justifies specialized care. The goal is never only to remove the mass: it is to remove it while preserving the nerve's function, both sensory and motor.
For a schwannoma
Treatment of a bothersome or growing schwannoma is surgical, and it gives excellent results. Because it is well defined, it can most often be enucleated under the microscope — separated from the nerve fibers it has pushed aside — leaving the nerve intact. After complete removal, the pain goes away and the risk of recurrence is low.
For a neurofibroma
The strategy is more nuanced. Because the neurofibroma is intertwined with the fibers, removing it can damage the nerve and cause a palsy. The decision is made case by case, weighing the discomfort, the pain, and the functional risk — sometimes by monitoring rather than operating right away.
Why this surgery cannot be improvised
Operating on a nerve tumor "blindly," without imaging or the right technique, risks a lasting deficit — a loss of sensation or strength in the nerve's territory.
This is microsurgery that requires precise mapping, magnifying equipment, and sometimes monitoring of the nerve's function during the procedure. The right move, in the right place, preserves the nerve; a hasty move can compromise it.
The signs that call for a closer look
This is the article's safety net. While the vast majority of these tumors are benign, a few signs should raise the possibility of a malignant or atypical form — rare, but one that completely changes management.
What should raise concern
—A mass that grows quickly, whereas benign tumors change very slowly.
—New, intense, or nighttime pain, different from the simple shocks of a benign tumor.
—The rapid onset or worsening of a deficit — loss of strength or sensation.
—A background of a predisposing genetic disease (neurofibromatosis), which warrants particular monitoring.
When these signs are present, the work-up is thorough — imaging, specialist opinion, planned biopsy if needed — because a malignant form, though rare, must be managed without delay and by specialists.
It bears repeating, so as not to cause needless worry: these signs are the exception. The rule, for a slow-growing nerve mass, remains by far the benign tumor.
Malignant forms, briefly
Malignant peripheral nerve sheath tumors are rare but serious. They call for specialized, multidisciplinary oncology care, of which surgery — complete removal with clear margins — remains the cornerstone, sometimes combined with other treatments. Their outlook is more guarded than that of benign tumors, and requires prolonged follow-up.
As this site focuses on hand and nerve surgery, this oncology care falls outside its scope: it is mentioned for completeness, but is handled by teams specialized in cancer care.
It should be kept in mind that a cancer (melanoma, lung cancer…) can be revealed by a metastasis in a nerve. The lesion in the nerve then points to the primary cancer.
The overall picture
This table sums up the article: almost always benign and curable while preserving the nerve; targeted vigilance for the rare malignant forms.
Recovery
The details depend on the procedure performed and the location of the tumor. To explore real-world cases, visit our knowledge center.
Frequently asked questions
Glossary
A mass growing on a nerve or its sheaths; most often benign.
The most common benign nerve tumor; well defined, often enucleable while preserving the nerve.
A benign tumor more intertwined with the nerve fibers, more delicate to remove.
Removal of a tumor by separating it from the nerve fibers, which are preserved.
A genetic disease that predisposes to nerve tumors; warrants particular monitoring.
A rare cancerous form of nerve tumor, calling for specialized oncology care.
References
Schwannoma of the Upper Limb (reviews 2013-2024) — the schwannoma is the most common tumor of the peripheral nerves (about 90 % of nerve tumors); encapsulated, it pushes the fascicles aside and allows enucleation while preserving the nerve
Surgical outcome of isolated benign peripheral nerve sheath tumors. Egypt J Neurosurg. 2024 — the schwannoma grows outside the bundles and can be enucleated; the neurofibroma is intertwined with the fibers and harder to remove without a deficit
Schwannoma of the Upper Limb: retrospective study. 2022 — curative treatment by enucleation; a preoperative biopsy is not indicated when a schwannoma is suspected, to avoid damaging the fascicles; MRI helpful for diagnosis in ~90 % of cases
Nerve Tumors of the Upper Extremity. Clin Plast Surg. 2019 — schwannomas, because they are encapsulated, lend themselves to intraneural dissection better than neurofibromas, allowing preservation of the nerve
Surgical Management of Sporadic Peripheral Nerve Schwannomas. 2021 — complete resection in 92.5 % of cases; improvement in pain and deficits in ~89 %; persistent motor deficit exceptional
Diagnosis and management of MPNST (reviews 2020-2025) — malignant peripheral nerve sheath tumors are rare but aggressive; warning signs: rapid growth, new pain, deficit; increased risk in type 1 neurofibromatosis
Long-term functional outcomes after enucleation of an upper-limb schwannoma
Monitoring of nerve tumors in neurofibromatosis
Reviewed and approved by Dr Frédéric Teboul, a surgeon of the hand, brachial plexus, and peripheral nerves, and a member of the Académie Nationale de Chirurgie.
Last updated: 20 August 2026
Disclaimer. This article is for information only. It does not replace a medical consultation. A mass that grows quickly, becomes painful, or comes with weakness deserves a specialist opinion without delay.
Author of this publication
Every piece of content is signed by its author and reviewed before publication.
 Author
Dr Frédéric Teboul
Hand surgeon — specialist in the brachial plexus and peripheral nerves